Tracheobronchial Malacia services offered in Miami, FL
Tracheobronchial Malacia: Incidence, Risk Factors, Types, and Causes
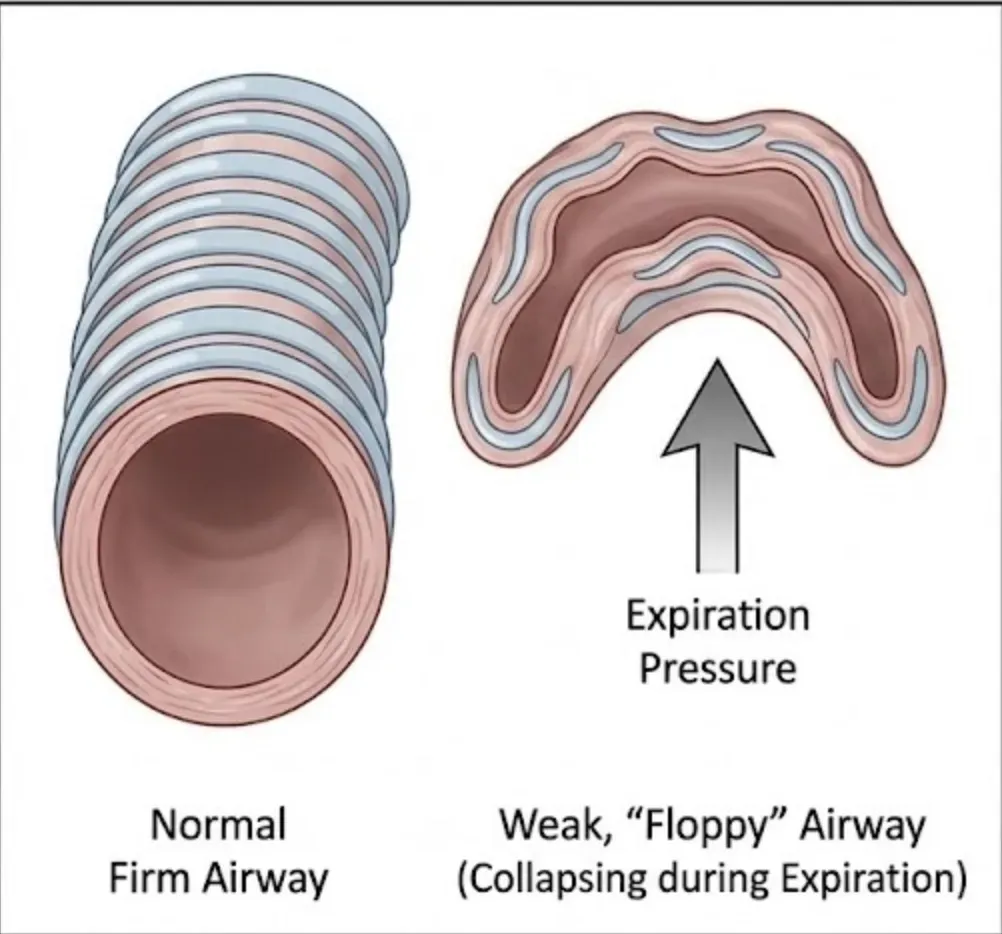
Tracheobronchial malacia (TBM) is an acquired or congenital disorder characterized by weakness of the tracheal and/or bronchial walls, resulting in excessive dynamic airway collapse, particularly during expiration.
- Incidence: The true incidence of TBM is difficult to establish because there is no universally accepted diagnostic threshold and many patients remain undiagnosed. It is increasingly recognized in adults evaluated for unexplained dyspnea, chronic cough, wheezing, recurrent respiratory infections, or symptoms that persist despite treatment for asthma or COPD. Significant expiratory central airway collapse has been reported in approximately 5–10% of patients undergoing evaluation for respiratory symptoms, with substantially higher rates in selected populations with chronic obstructive pulmonary disease.
- Patients at Risk: TBM is most commonly recognized in older adults and in patients with chronic pulmonary disease, particularly COPD and asthma. Other risk groups include patients with a history of prolonged mechanical ventilation or tracheostomy, prior airway or thoracic surgery, recurrent respiratory infections, connective-tissue disorders, and significant chronic inflammation of the airways.
- Types of TBM:
- Tracheomalacia – weakness and excessive collapse of the tracheal wall.
- Bronchomalacia – weakness involving one or more main or lobar bronchi.
- Tracheobronchomalacia – involvement of both the trachea and bronchi.
- Excessive dynamic airway collapse (EDAC) – excessive inward displacement of the posterior membranous wall of the trachea and/or bronchi during expiration, with relatively preserved cartilage. EDAC and malacia can coexist and are often considered within the spectrum of expiratory central airway collapse.
- Causes: TBM may be congenital or acquired. Acquired disease is more common in adults and may result from chronic airway inflammation, COPD, recurrent infection, prolonged mechanical ventilation, tracheostomy, endotracheal tube injury, prior thoracic or airway surgery, chest trauma, or external compression of the airway. Less common causes include relapsing polychondritis and other connective-tissue disorders, inflammatory or infiltrative diseases, and malignancy. In some patients, no specific underlying cause can be identified, and the condition is considered idiopathic.
Presenting Symptoms of Tracheobronchomalacia
Patients with tracheobronchomalacia (TBM) may present with a broad range of respiratory symptoms, and the condition is frequently mistaken for or attributed to asthma, COPD, chronic bronchitis, or recurrent respiratory infections. Symptoms generally result from dynamic narrowing of the trachea and/or main bronchi during expiration, which impairs airflow and secretion clearance.
Common presenting symptoms include:
- Progressive or unexplained shortness of breath, particularly with exertion.
- Chronic cough, often described as harsh, barking, or brassy.
- Wheezing or noisy breathing, which may be mistaken for asthma and may not respond adequately to conventional bronchodilator therapy.
- Difficulty clearing airway secretions, resulting in a sensation of mucus retention or frequent throat/chest clearing.
- Recurrent bronchitis or respiratory infections, related to impaired clearance of secretions.
- Chest congestion and excessive sputum production, particularly during respiratory infections.
- Exercise intolerance and reduced functional capacity, often disproportionate to conventional pulmonary-function testing.
- Orthopnea or worsening symptoms when supine in some patients.
- Cough or dyspnea triggered by exertion, coughing, or forced expiration.
- Episodes of acute respiratory distress or difficulty breathing, particularly during respiratory infections.
A characteristic feature is that symptoms may be disproportionate to the findings on routine pulmonary testing or chest imaging. Some patients have persistent symptoms despite appropriate treatment for asthma or COPD. In severe disease, patients may develop a sensation of inability to take a deep breath, marked exercise limitation, or difficulty recovering from respiratory infections.
From a clinical standpoint, persistent dyspnea, cough, wheezing, recurrent respiratory infections, or impaired secretion clearance—especially when these symptoms remain unexplained or refractory to conventional treatment—should raise suspicion for TBM or another form of expiratory central airway collapse.
Tracheobronchial Malacia Q&A
The Institute for Thoracic Surgery in Miami, Florida is one of a handful of centers that evaluate and offer state of the art surgical care for patients suffering from tracheobronchial malacia. Mark R. Dylewski, M.D., provides specialized evaluation and minimally invasive surgical treatment for patients with symptoms suggestive of Tracheobronchial malacia.
Evaluation and Treatment of Tracheobronchomalacia
Evaluation: Patients with suspected tracheobronchomalacia (TBM) commonly present with unexplained exertional dyspnea, chronic cough, wheezing, difficulty clearing secretions, recurrent respiratory infections, or persistent respiratory symptoms despite appropriate treatment for asthma or COPD. Evaluation should begin with a detailed history and pulmonary examination, assessment for coexisting pulmonary and upper-airway disorders, pulmonary function testing, and imaging. The diagnosis is best established with dynamic inspiratory and expiratory CT of the chest and dynamic flexible bronchoscopy, performed with spontaneous breathing and forced expiration/coughing to directly assess the degree and distribution of airway collapse.
Importantly, the degree of anatomic collapse must be interpreted in conjunction with the patient's symptoms. Although a ≥50% reduction in airway cross-sectional area has historically been used as a diagnostic threshold, substantial collapse can occur in otherwise healthy individuals. Patients being considered for surgical treatment generally have severe, symptomatic disease with near-complete or >90% dynamic collapse of the trachea and/or main bronchi. In selected patients, a temporary airway-stent trial may be used as a physiologic test to determine whether stabilization of the airway is likely to improve symptoms.
Treatment
Treatment should be individualized according to the severity of airway collapse, symptoms, underlying disease, and overall functional status. Initial management includes optimization of associated conditions such as COPD, asthma, gastroesophageal reflux, and vocal-cord dysfunction, together with pulmonary rehabilitation, airway-clearance therapy, treatment of respiratory infections, and, in selected patients, CPAP or other forms of pneumatic airway splinting. Surgical stabilization is generally reserved for highly symptomatic patients with severe TBM/expiratory central airway collapse who remain significantly impaired despite appropriate medical management.
Tracheobronchoplasty
Tracheobronchoplasty (TBP) is the definitive surgical procedure for appropriately selected patients with severe diffuse TBM. The operation restores the normal configuration and rigidity of the central airway by plicating the redundant posterior membranous wall and reinforcing the weakened tracheal and bronchial cartilage with a supportive mesh or prosthetic material. This stabilizes the airway and reduces excessive expiratory collapse.
Open tracheobronchoplasty has traditionally been performed through a right posterolateral thoracotomy. This approach provides extensive exposure of the trachea and main bronchi and remains an established treatment for severe disease. However, thoracotomy can be associated with substantial postoperative pain, pulmonary morbidity, longer hospitalization, and a prolonged recovery—particularly in patients who frequently have significant underlying cardiopulmonary disease.
Traditional VATS tracheobronchoplasty provides a minimally invasive alternative to thoracotomy. Early VATS experience demonstrated the feasibility of thoracoscopic airway stabilization, although the technical demands of suturing and mesh placement around the central airways have limited widespread adoption compared with robotic techniques.
Robotic-assisted tracheobronchoplasty has increasingly become an important minimally invasive approach. The robotic platform provides high-definition three-dimensional visualization, magnification, and articulated wristed instruments that facilitate precise dissection, posterior membranous-wall plication, and mesh fixation around the trachea and main bronchi. These capabilities can potentially reduce the morbidity associated with an open thoracotomy while maintaining the principles of a complete airway stabilization procedure.
Outcomes
The available literature demonstrates that appropriately selected patients undergoing tracheobronchoplasty can experience substantial improvement in respiratory symptoms, quality of life, exercise capacity, and objective airway patency. In an early series of 42 robotic procedures, median hospital stay was 3 days, there was no 90-day mortality, and postoperative testing demonstrated improvements in FEV1, FVC, and peak expiratory flow; 82% of patients reported overall satisfaction with the procedure.
More recent long-term data demonstrate that both open and robotic TBP can produce durable reduction in dynamic airway collapse, with meaningful improvement in functional exercise capacity. In a 61-patient cohort, both approaches produced marked improvement in bronchoscopic measures of airway collapse, while six-minute walk distance improved by an average of approximately 76 meters at two years.
The available evidence also suggests that symptom and quality-of-life improvement may be more consistent than improvement in conventional pulmonary-function measurements. Robotic surgery appears to offer the potential advantages of less invasive access and shorter recovery while achieving airway stabilization comparable to open repair, although most comparative studies remain retrospective and longer-term comparative data are still evolving.
In summary: Successful treatment of TBM depends on careful patient selection, objective confirmation of severe dynamic airway collapse, optimization of coexisting pulmonary disease, and evaluation by an experienced multidisciplinary airway team. For patients with severe symptomatic disease, tracheobronchoplasty—particularly through a minimally invasive robotic approach—can provide durable airway stabilization with meaningful improvements in symptoms, quality of life, and functional capacity while significantly reducing potential complications from traditional open surgery.