Mediastinal Mass services offered in Miami, FL
Mediastinal masses can represent a wide range of benign and malignant conditions and may affect the heart, lungs, airway, esophagus, blood vessels, and other vital structures within the chest. At the Institute for Thoracic Surgery in Miami, Florida, Mark R. Dylewski, M.D., provides specialized surgical evaluation and treatment for patients with mediastinal masses, including tumors and other complex disorders involving the thymus, lymph nodes, nerves, and surrounding mediastinal structures. His approach incorporates advanced imaging, multidisciplinary evaluation, and minimally invasive surgical techniques whenever appropriate, with treatment tailored to the specific diagnosis, location, size, and extent of the mass. When surgery is indicated, Dr. Dylewski utilizes modern thoracic surgical approaches, including robotic-assisted and video-assisted thoracic surgery (VATS), as well as open surgery when necessary, with the goal of achieving safe and complete treatment while minimizing surgical trauma.
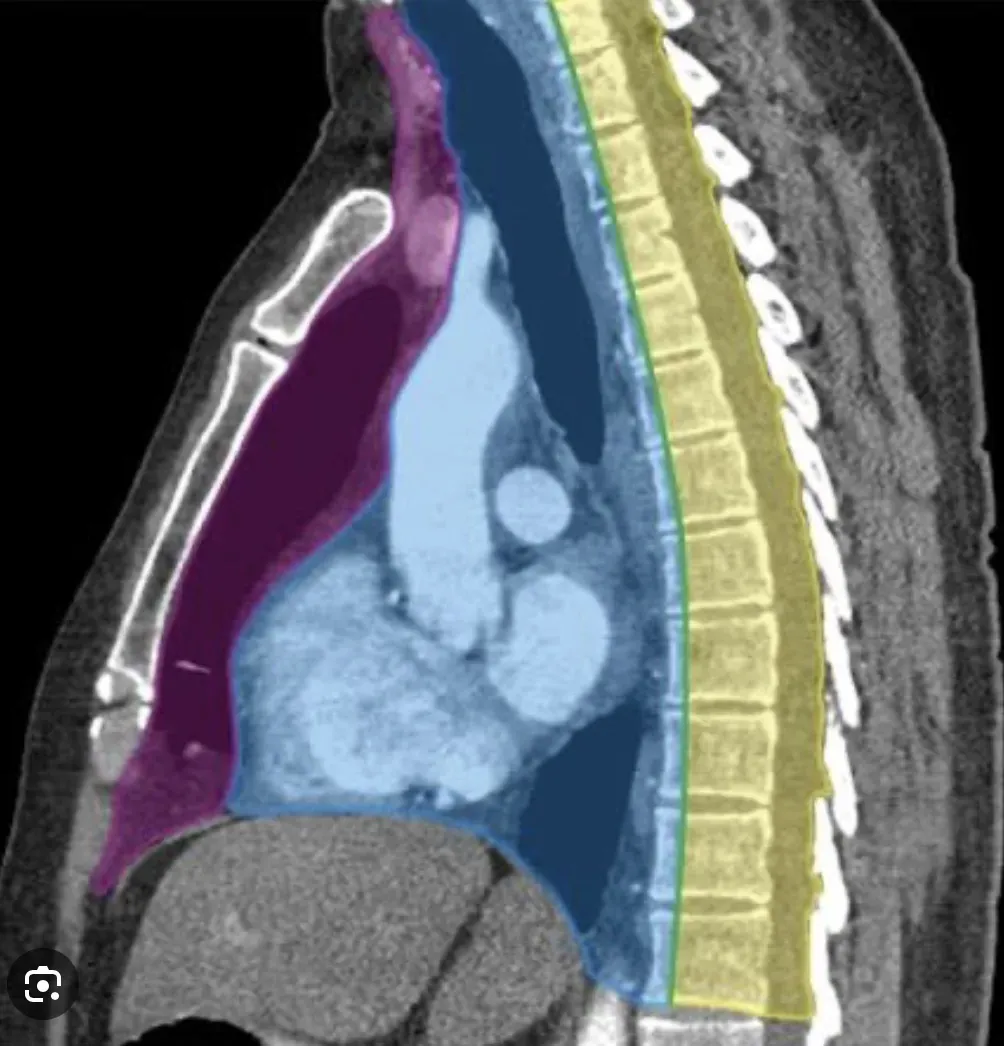
Mediastinal masses represent a diverse group of benign and malignant lesions arising from the thymus, lymphatic system, nerves, germ cells, thyroid or parathyroid tissue, esophagus, tracheobronchial tree, vascular structures, and other mediastinal tissues. Traditionally, the mediastinum has been divided into four compartments—superior, anterior, middle, and posterior—although the contemporary CT-based classification endorsed by the International Thymic Malignancy Interest Group (ITMIG) uses three compartments: prevascular, visceral, and paravertebral. In the traditional four-compartment model, the superior mediastinum contains the thymic remnants, great vessels, trachea, esophagus, lymphatic structures, and nerves and may harbor thyroid or parathyroid lesions, lymphadenopathy, lymphoma, metastatic disease, vascular abnormalities, and other masses. The anterior mediastinum contains primarily thymic tissue, fat, and lymph nodes and is classically associated with thymic tumors and cysts, lymphoma, germ-cell tumors, and thyroid or parathyroid lesions. The middle mediastinum contains the heart, pericardium, great vessels, trachea, main bronchi, and lymph nodes and may give rise to bronchogenic or pericardial cysts, vascular lesions, lymphadenopathy, and lesions involving the airway, esophagus, or cardiovascular structures. The posterior mediastinum contains the esophagus, thoracic aorta, sympathetic chain, and other neural structures and is particularly associated with neurogenic tumors, including schwannomas and neurofibromas, as well as esophageal, vascular, osseous, and paravertebral abnormalities. The etiology of a mediastinal mass may therefore be neoplastic, congenital, infectious, inflammatory, vascular, or traumatic, with the differential diagnosis influenced substantially by the patient's age, clinical history, anatomic location, and imaging characteristics. Risk factors vary according to the underlying disease and may include increasing age, tobacco exposure, prior malignancy, immunosuppression, previous radiation therapy, autoimmune disease, and conditions associated with chronic infection or inflammation. Patients may be asymptomatic, with a mass discovered incidentally on chest radiography or CT, or may present with chest pain or pressure, cough, dyspnea, wheezing, dysphagia, hoarseness, recurrent respiratory infections, or symptoms related to airway, esophageal, vascular, or nerve compression. Constitutional symptoms such as fever, night sweats, fatigue, and unexplained weight loss may suggest lymphoma, infection, or another systemic process. Accurate localization of the mass, followed by characterization with contrast-enhanced CT and, when appropriate, MRI, laboratory evaluation, PET/CT, or tissue diagnosis, is essential for establishing the etiology and guiding multidisciplinary treatment.