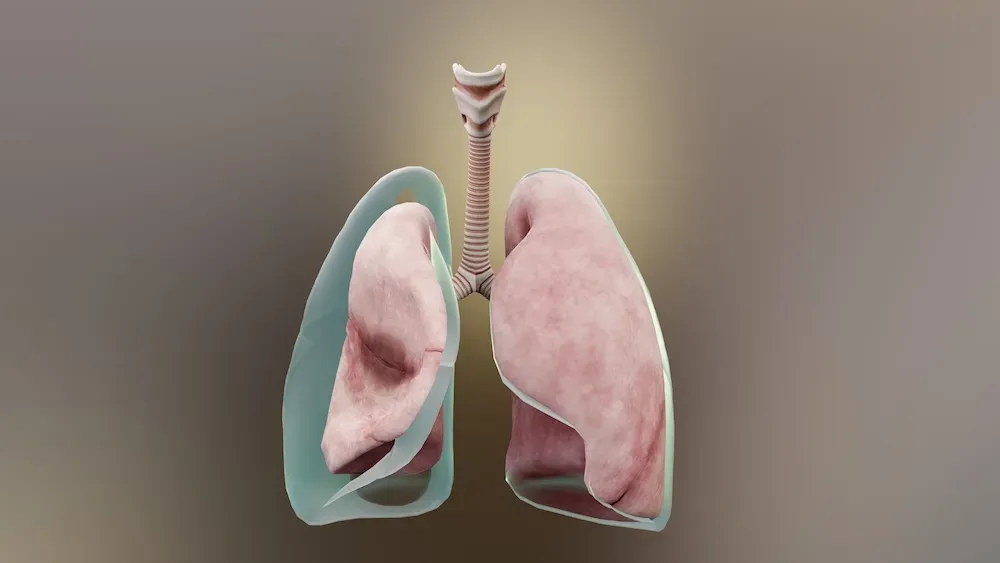
Pneumothorax Surgery services offered in Miami, FL
Pneumothorax Surgery
A pneumothorax, commonly referred to as a collapsed lung, occurs when air enters the space between the lung and chest wall, causing the lung to partially or completely collapse. Although some pneumothoraces can be managed with observation, oxygen therapy, or drainage of the trapped air, certain patients require surgical treatment to achieve definitive management and reduce the risk of recurrence.
At the Institute for Thoracic Surgery in Miami, Florida, Mark R. Dylewski, M.D., provides specialized surgical care for patients with recurrent, persistent, or complicated pneumothoraces. The decision to proceed with surgery depends on the cause of the pneumothorax, its severity, whether it has recurred, and the patient's overall clinical condition.
When surgery is indicated, the goal is to identify and address the underlying source of the air leak, allow the lung to fully re-expand, and reduce the likelihood of another pneumothorax. In appropriately selected patients, these procedures can often be performed using advanced minimally invasive techniques, including video-assisted thoracoscopic surgery (VATS) or robotic-assisted thoracic surgery.
If you have experienced a pneumothorax or have been diagnosed with a recurrent or persistent collapsed lung, a specialized thoracic surgical evaluation can help determine the most appropriate treatment. Contact the Institute for Thoracic Surgery to schedule a consultation with Dr. Dylewski and discuss your treatment options.
Pneumothorax Surgery Q&A
Pneumothorax
A pneumothorax, commonly known as a collapsed lung, occurs when air enters the pleural space—the area between the lung and chest wall. As air accumulates in this space, it can prevent the lung from fully expanding and, in some cases, cause a partial or complete collapse.
A pneumothorax can occur for a number of reasons. Some develop spontaneously in otherwise healthy individuals, while others are associated with underlying lung disease, trauma, or medical procedures. Regardless of the cause, appropriate evaluation is important to determine the severity of the pneumothorax, identify its underlying cause, and determine the most appropriate treatment.
At the Institute for Thoracic Surgery in Miami, Florida, Mark R. Dylewski, M.D., provides specialized evaluation and surgical treatment for patients with recurrent, persistent, or complicated pneumothoraces. When surgery is indicated, he uses advanced minimally invasive techniques whenever appropriate, including video-assisted thoracoscopic surgery (VATS).
Why Does a Pneumothorax Occur?
Pneumothoraces have several possible causes. Understanding why the lung has collapsed is an important part of determining treatment and the risk of recurrence.
Primary Spontaneous Pneumothorax
A primary spontaneous pneumothorax occurs without an obvious underlying lung disease. It can develop when small, fragile air-filled areas on the surface of the lung, known as blebs, rupture and allow air to escape into the pleural space.
Primary spontaneous pneumothorax is more common in younger, otherwise healthy individuals and occurs more frequently in people who smoke. Smoking is an important risk factor because it can contribute to the development of abnormalities in the lung that increase the likelihood of pneumothorax and recurrence.
Secondary Spontaneous Pneumothorax
A secondary spontaneous pneumothorax occurs in association with an underlying lung condition. Diseases that can increase the risk include:
- Chronic obstructive pulmonary disease (COPD) and emphysema
- Asthma
- Cystic fibrosis
- Interstitial lung disease
- Certain lung infections
- Other conditions that damage or weaken lung tissue
In these patients, even a relatively small pneumothorax can have a more significant effect on breathing because underlying lung function may already be compromised.
Traumatic Pneumothorax
A pneumothorax can also result from an injury to the chest. Blunt or penetrating trauma, including injuries sustained in motor vehicle accidents or falls, can damage the lung and allow air to enter the pleural space.
Procedure-Related Pneumothorax
A pneumothorax can occasionally occur as a complication of a medical procedure involving the chest or lungs. Examples include certain lung biopsies, placement of central venous catheters, or other procedures that involve the thorax.
How Is a Pneumothorax Treated?
Treatment depends on the size and severity of the pneumothorax, the patient's symptoms, the underlying cause, whether there is an ongoing air leak, and whether the pneumothorax has occurred previously.
Observation
A small, stable pneumothorax may sometimes be managed with observation and follow-up imaging, particularly when the patient has minimal symptoms and is clinically stable. The body can gradually reabsorb the air from the pleural space, allowing the lung to re-expand.
Needle Aspiration or Chest Tube
A larger or symptomatic pneumothorax may require removal of the trapped air. Depending on the circumstances, this may be accomplished with needle aspiration or placement of a chest tube into the pleural space.
A chest tube allows air to escape while the lung re-expands. The patient is monitored for resolution of the air leak and restoration of normal lung expansion.
Surgery
Surgery may become appropriate when the pneumothorax does not resolve with less invasive treatment, when an air leak persists, when the lung does not fully re-expand, or when there is a significant risk of recurrence.
Surgery is also considered in certain patients after a recurrent pneumothorax or when the circumstances of the patient's condition make prevention of another episode particularly important.
The decision is individualized based on the patient's medical history, underlying lung condition, previous pneumothoraces, imaging findings, occupation or activities, and overall health.
When Is Pneumothorax Surgery Recommended?
Dr. Dylewski may recommend surgical treatment when:
- The pneumothorax has recurred
- An air leak persists despite chest-tube treatment
- The lung does not fully re-expand
- Imaging identifies blebs, bullae, or other abnormal areas of lung that may be responsible for the air leak
- There is a significant concern for another pneumothorax
- The patient's underlying condition or circumstances make recurrence particularly problematic
The primary goals of surgery are to identify and eliminate the source of the air leak, allow the lung to remain fully expanded, and reduce the likelihood of future pneumothorax.
What Happens During Pneumothorax Surgery?
When surgery is appropriate, Dr. Dylewski generally uses a minimally invasive approach whenever technically suitable. Video-assisted thoracoscopic surgery (VATS) is performed under general anesthesia through several small incisions between the ribs.
A small thoracoscopic camera provides visualization inside the chest, allowing the surgeon to identify the source of the air leak and any abnormal areas of lung.
Depending on the underlying cause, surgery may involve removing abnormal portions of lung containing blebs or bullae, which are fragile, air-filled areas that can rupture and cause a pneumothorax.
The procedure may also include pleurodesis, a technique designed to promote adherence between the lung and the chest wall. Pleurodesis reduces the potential space in which air can accumulate and is used to decrease the risk of recurrent pneumothorax in appropriately selected patients.
In certain circumstances, other surgical techniques may be necessary based on the underlying anatomy or cause of the pneumothorax.
Recovery After Pneumothorax Surgery
Following surgery, patients are monitored in the hospital while the lung re-expands and the surgical team monitors for an ongoing air leak. A chest tube is generally left temporarily to drain air and fluid from the pleural space and to confirm that the lung remains fully expanded.
Patients are encouraged to walk, perform breathing exercises, and gradually increase their activity as appropriate. Pain management is an important part of recovery and may include a combination of medications and other strategies.
Recovery varies depending on the extent of surgery, the patient's underlying lung function, and overall health. Minimally invasive surgery generally results in less chest-wall disruption than a traditional open thoracotomy and may facilitate recovery.
Before discharge, patients receive individualized instructions regarding wound care, activity restrictions, driving, exercise, work, and follow-up.
Reducing the Risk of Recurrence
One of the important goals of surgical treatment is to reduce the likelihood of another pneumothorax. This is particularly relevant for patients who have experienced recurrent episodes or who have identifiable blebs, bullae, or other structural abnormalities of the lung.
Smoking cessation is also an important component of reducing future risk. Continued smoking can increase the likelihood of developing another pneumothorax and can contribute to progressive lung damage.
Specialized Surgical Care for Pneumothorax
A pneumothorax is not always a surgical condition. Some patients can be successfully treated with observation, while others require aspiration or chest-tube drainage. For patients with persistent air leaks, recurrent pneumothoraces, or structural abnormalities of the lung, surgery may provide a definitive approach to addressing the underlying source of the problem.
At the Institute for Thoracic Surgery, Dr. Dylewski evaluates each patient individually to determine the cause of the pneumothorax and identify the treatment strategy most appropriate for their circumstances. When surgery is indicated, the goal is to eliminate the source of the air leak, preserve healthy lung tissue, and minimize the risk of recurrence using the least invasive approach that can safely achieve these objectives.
If you have experienced a pneumothorax, particularly a recurrent or persistent collapsed lung, a consultation with a thoracic surgeon can help determine whether additional treatment or surgery is appropriate.