Thoracic Outlet Syndrome services offered in Miami, FL
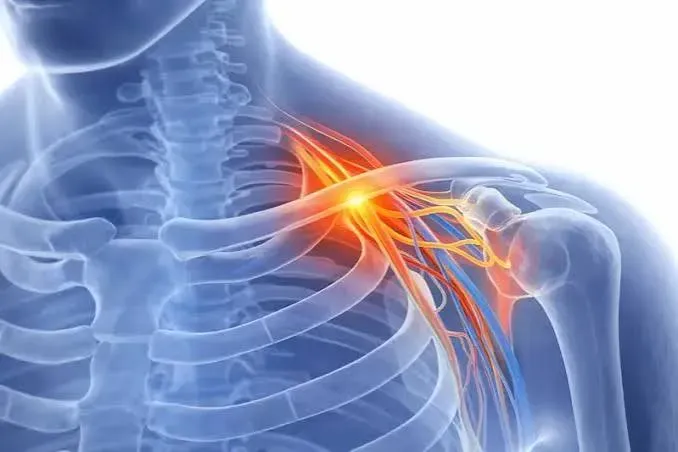
Thoracic outlet syndrome (TOS) refers to compression of the nerves or blood vessels as they pass through the thoracic outlet—the space between the lower neck, first rib, and shoulder. It is generally classified into three main types:
- Neurogenic TOS: The most common form, caused by compression of the brachial plexus nerves. Symptoms may include neck, shoulder, or arm pain, numbness, tingling, weakness, and hand fatigue.
- Venous TOS: Compression of the subclavian vein can cause arm swelling, heaviness, discoloration, or venous thrombosis. It is sometimes associated with repetitive overhead activity.
- Arterial TOS: The least common form, caused by compression of the subclavian artery. It may produce hand or arm pain, coldness, discoloration, numbness, or reduced circulation and can be associated with arterial damage or aneurysm.
Thoracic outlet syndrome may be related to anatomical abnormalities such as a cervical rib, abnormal first rib or scalene muscles, trauma, repetitive overhead activity, or other structural factors. Accurate diagnosis is important because treatment differs substantially according to whether the nerves, vein, or artery is involved.
Thoracic Outlet Syndrome Q&A
Evaluation and Treatment of Thoracic Outlet Syndrome
Thoracic outlet syndrome (TOS) is a group of disorders caused by compression of the nerves or blood vessels passing between the neck and upper chest. The three principal forms are neurogenic, venous, and arterial thoracic outlet syndrome. Because the symptoms and underlying anatomy can differ substantially, accurate diagnosis is essential before treatment is selected.
How Is Thoracic Outlet Syndrome Evaluated?
Evaluation begins with a detailed medical history and physical examination. The physician assesses the distribution of pain, numbness, weakness, swelling, or vascular symptoms and examines the neck, shoulder, arm, and hand. Provocative maneuvers, including the elevated arm stress test and Tinel's sign over the supraclavicular region, may help support a diagnosis of neurogenic TOS. A cervical spine or chest X-ray may be obtained to identify a cervical rib or other bony abnormality.
Additional testing is selected according to the suspected type of TOS. Ultrasound, CT angiography, MR angiography, or other vascular studies may be used to evaluate arterial or venous compression, thrombosis, or vascular injury. Electrodiagnostic testing may help evaluate nerve function or exclude other causes of arm and hand symptoms. MRI can also be useful in selected patients to evaluate the brachial plexus or identify alternative diagnoses.
Treatment of Neurogenic Thoracic Outlet Syndrome
Neurogenic TOS is the most common form and results from compression or irritation of the brachial plexus. Initial treatment is generally conservative and may include specialized physical therapy, postural correction, stretching and strengthening of the shoulder girdle, nerve-gliding exercises, and modification of activities that reproduce symptoms. A period of nonoperative treatment is generally recommended before surgery when there is no significant neurologic deficit.
Surgery may be considered when symptoms persist despite appropriate conservative treatment or when there is significant weakness, muscle atrophy, persistent neurologic deficit, or a correctable structural abnormality. Surgical decompression may involve removal of a cervical rib or abnormal band, division or removal of portions of the scalene muscles, brachial plexus neurolysis, and, in selected patients, first-rib resection. There remains variation among experienced surgeons regarding when first-rib resection is necessary, making individualized evaluation particularly important.
Treatment of Venous Thoracic Outlet Syndrome
Venous TOS occurs when the subclavian vein is compressed and may cause arm swelling, heaviness, discoloration, or venous thrombosis. Evaluation commonly includes duplex ultrasound and, when necessary, advanced venous imaging to define the location and severity of compression.
Patients with acute thrombosis may require anticoagulation and, in selected cases, thrombolytic or catheter-based treatment. Definitive management of significant venous compression may require surgical decompression, frequently involving first-rib resection and removal of the structures responsible for compression. Treatment may be coordinated with vascular specialists when venous reconstruction or additional intervention is necessary.
Treatment of Arterial Thoracic Outlet Syndrome
Arterial TOS is less common but can cause compromised blood flow to the arm or hand. Patients may develop pain, coldness, discoloration, numbness, diminished pulses, or other signs of arterial insufficiency. Imaging is particularly important to identify arterial compression, aneurysm, thrombosis, or other vascular damage.
Treatment generally focuses on relieving the underlying compression and addressing any arterial injury. Surgical decompression may include first-rib or cervical-rib resection and removal of abnormal bands or muscles. When the artery has sustained significant damage, vascular reconstruction or repair may be required as part of the same treatment strategy.
Surgical Approaches for Thoracic Outlet Syndrome
Several surgical approaches have been developed for thoracic outlet decompression. The choice depends on the structures involved, the location of compression, prior surgery, vascular involvement, and the surgeon's assessment of the safest method to achieve complete decompression.
Open Supraclavicular Approach:
The supraclavicular approach uses an incision above the collarbone and provides direct exposure of the brachial plexus, scalene muscles, first rib, and adjacent vascular structures. It is particularly useful when detailed exposure of the nerves and surrounding anatomy is required and can be adapted to complex neurogenic or vascular disease. Current consensus recommendations for neurogenic TOS favor an anterior supraclavicular approach for exposure of the supraclavicular brachial plexus.
Transaxillary or Axillary Approach:
The transaxillary approach accesses the first rib through an incision in the armpit. It has historically been used for first-rib resection and can avoid a visible incision at the base of the neck. Its principal limitation is more restricted visualization of certain structures, particularly the brachial plexus and portions of the subclavian vessels.
Robotic-Assisted Thoracic Approach:
Robotic-assisted thoracic surgery provides another minimally invasive route to the thoracic outlet in selected patients. Through several small chest incisions, the surgeon can use a high-definition, magnified three-dimensional camera and articulated instruments to perform procedures such as first-rib resection and decompression.
One potential advantage of the robotic approach is enhanced visualization and instrument articulation within the confined anatomy of the thoracic outlet. The robotic platform can provide an enlarged three-dimensional view and allow precise dissection around the first rib, scalene muscles, pleura, and neurovascular structures. It may also permit the procedure to be performed through small incisions rather than a larger open exposure. Robotic first-rib resection has been described for selected patients with venous and other forms of TOS.
Robotic surgery, however, is not automatically appropriate for every patient. The optimal approach depends on the specific anatomy and type of compression. In some patients, an open supraclavicular operation provides superior access to the brachial plexus or vascular structures, while a minimally invasive or robotic approach may be advantageous for selected intrathoracic components of the operation.
Individualized Treatment
Successful treatment of thoracic outlet syndrome depends on identifying what structure is being compressed, where the compression occurs, and why it is occurring. Treatment may involve physical therapy, vascular intervention, medications, or surgery, and complex cases may require coordination among thoracic surgery, vascular surgery, neurology, radiology, and physical therapy.
When surgery is necessary, the objective is to achieve complete and durable decompression while minimizing surgical trauma. The surgical approach—supraclavicular, transaxillary, open, minimally invasive, or robotic—is selected according to the patient's anatomy and the specific form of thoracic outlet syndrome rather than simply the availability of a particular technology.