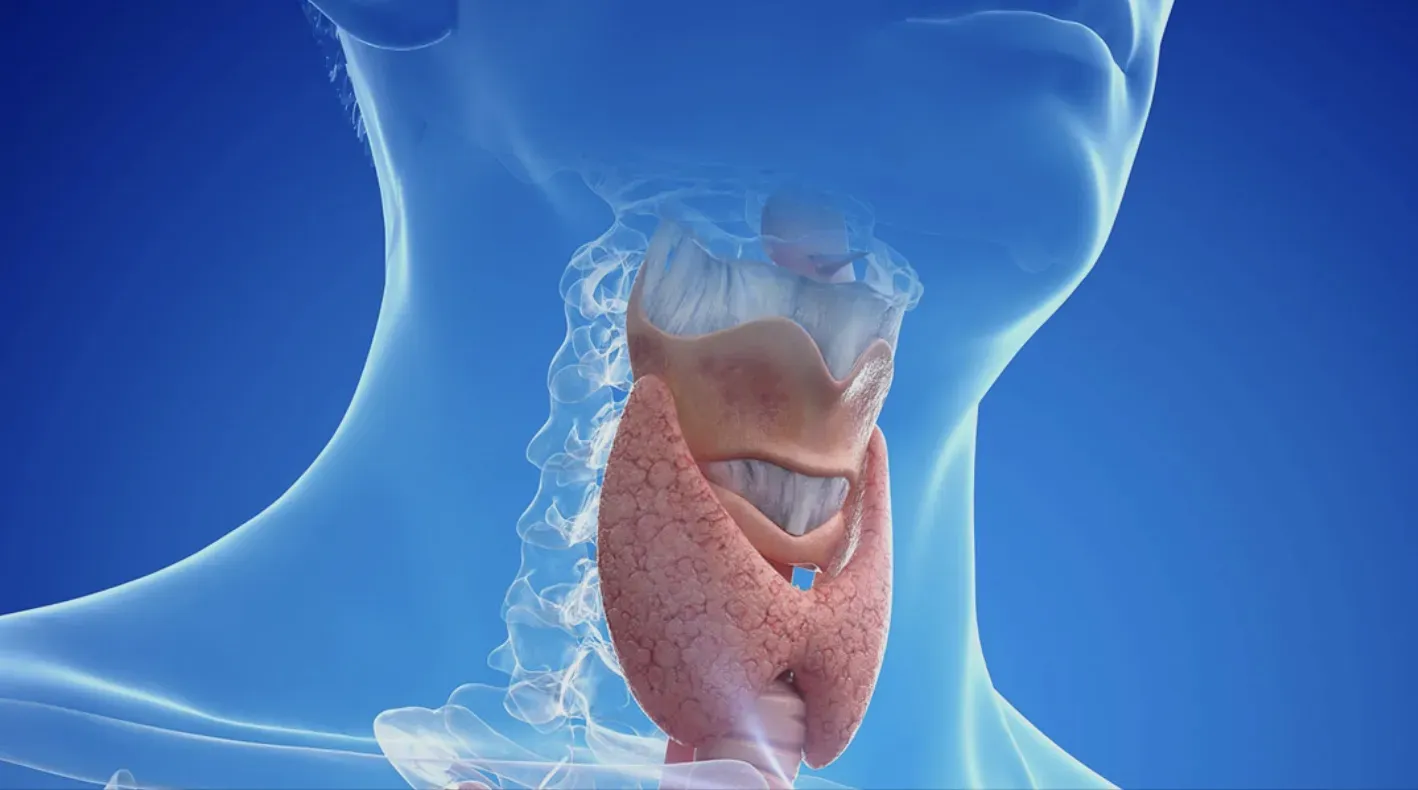
Thyroid Mass services offered in Miami, FL
Thyroid masses can range from benign thyroid nodules and cysts to thyroid malignancies and may occasionally extend into the chest, where they can affect the airway, esophagus, and other vital mediastinal structures. At the Institute for Thoracic Surgery in Miami, Florida, Mark R. Dylewski, M.D., provides specialized surgical evaluation and treatment for patients with complex thyroid masses, including lesions with substantial substernal or intrathoracic extension. His approach incorporates advanced imaging, comprehensive diagnostic evaluation, and multidisciplinary collaboration to determine the appropriate treatment for each patient. When surgical intervention is indicated, Dr. Dylewski utilizes contemporary minimally invasive and thoracic surgical techniques when appropriate, with open surgery reserved for cases in which it is necessary to safely and completely remove the mass while protecting surrounding structures.
Thyroid Mass Q&A
Thyroid Masses: Causes, Evaluation, and Surgical Treatment
Thyroid masses encompass a broad spectrum of benign and malignant disorders, ranging from common thyroid nodules and cysts to inflammatory disease and thyroid cancer. The most common cause is benign nodular thyroid disease, including colloid nodules, thyroid cysts, and follicular adenomas. Other causes include multinodular goiter, Hashimoto thyroiditis, Graves disease, thyroiditis, parathyroid lesions, and primary thyroid malignancies, including papillary, follicular, medullary, and anaplastic thyroid carcinoma. Thyroid enlargement may also extend below the thoracic inlet into the superior mediastinum, producing a substernal or intrathoracic goiter. Less commonly, a thyroid mass may represent metastatic disease or other unusual tumors.
Patients may be asymptomatic, with a thyroid nodule discovered incidentally on physical examination or imaging. When symptoms occur, they may result from hormonal dysfunction, enlargement of the gland, or compression of adjacent structures. Common symptoms include a neck mass or fullness, difficulty swallowing, pressure in the neck, cough, shortness of breath, hoarseness, or discomfort. Large or substernal thyroid masses may compress or displace the trachea and esophagus and can occasionally produce significant respiratory or swallowing difficulties. Symptoms of hyperthyroidism or hypothyroidism may also occur depending on thyroid function. Rapid enlargement, firmness, fixation, cervical lymphadenopathy, persistent hoarseness, or symptoms of airway compromise warrant careful evaluation for malignancy or invasive disease.
Diagnostic Evaluation
The evaluation begins with a detailed history and physical examination, including assessment of the thyroid and cervical lymph nodes. Thyroid function testing, particularly TSH and free T4, helps determine whether the mass is associated with hyperthyroidism, hypothyroidism, or normal thyroid function. High-resolution thyroid and cervical ultrasound is the principal imaging study for most thyroid nodules. Ultrasound evaluates the size, composition, margins, echogenicity, calcifications, vascularity, and other characteristics that help determine the likelihood of malignancy and whether biopsy is indicated. Ultrasound can also evaluate regional cervical lymph nodes.
When a nodule has suspicious ultrasound characteristics or meets established size criteria, ultrasound-guided fine-needle aspiration (FNA) is commonly performed for cytologic evaluation. Selected indeterminate nodules may undergo molecular testing to further characterize the likelihood of malignancy and assist with surgical decision-making. A radionuclide thyroid scan may be appropriate in patients with a suppressed TSH to determine whether a nodule is hyperfunctioning. Hyperfunctioning nodules are generally associated with a lower likelihood of malignancy than nonfunctioning nodules.
CT or MRI becomes particularly important when there is a large goiter, substernal or mediastinal extension, suspected invasion, significant airway or esophageal compression, or concern for involvement of major vascular structures. CT provides excellent anatomic definition of the relationship between a large thyroid mass and the trachea, esophagus, great vessels, and mediastinum. In selected patients, laryngoscopy is performed to evaluate vocal-cord function, particularly when hoarseness is present or when surgery may place the recurrent laryngeal nerves at risk. Evaluation of serum calcitonin and other disease-specific studies may be considered when medullary thyroid carcinoma is suspected.
Surgical Treatment
The appropriate operation depends on the size and location of the mass, symptoms, thyroid function, cytologic diagnosis, presence of malignancy, lymph-node involvement, and extent of substernal or mediastinal extension. Many small, benign, asymptomatic thyroid nodules can be safely observed with periodic clinical examination and ultrasound rather than undergoing surgery. Surgery is generally considered for lesions that are malignant or suspicious for malignancy, symptomatic, enlarging, cosmetically significant, associated with compressive symptoms, or associated with substantial substernal extension.
The principal operations include thyroid lobectomy (hemithyroidectomy) and total thyroidectomy. Lobectomy is appropriate for selected unilateral nodules and some differentiated thyroid cancers, whereas total thyroidectomy may be recommended for selected bilateral disease, larger or more extensive malignancies, certain high-risk tumors, and other specific clinical circumstances. Patients with thyroid cancer and clinically significant cervical lymph-node disease may also require central or lateral compartment neck dissection.
For large substernal or intrathoracic goiters, most lesions can be removed through a cervical incision; however, a sternotomy or other thoracic approach may occasionally be necessary when the mass extends deeply into the mediastinum, particularly when it is large, extends below the aortic arch, is located posterior to major vascular structures, or cannot be safely mobilized through the neck. In appropriately selected cases, minimally invasive or robotic-assisted approaches may have a role, although the approach must be individualized according to the anatomy and oncologic requirements.
For malignant thyroid disease, surgery is frequently part of a multidisciplinary treatment strategy that may also include radioactive iodine, external-beam radiation therapy, systemic targeted therapy, immunotherapy, or active surveillance depending on tumor type and stage. The primary surgical objectives are complete and oncologically appropriate removal of disease while preserving critical structures, particularly the recurrent and superior laryngeal nerves, parathyroid glands, trachea, esophagus, and major vascular structures.